Monday, May 28, 2007

Treatment of Pathological Gambling

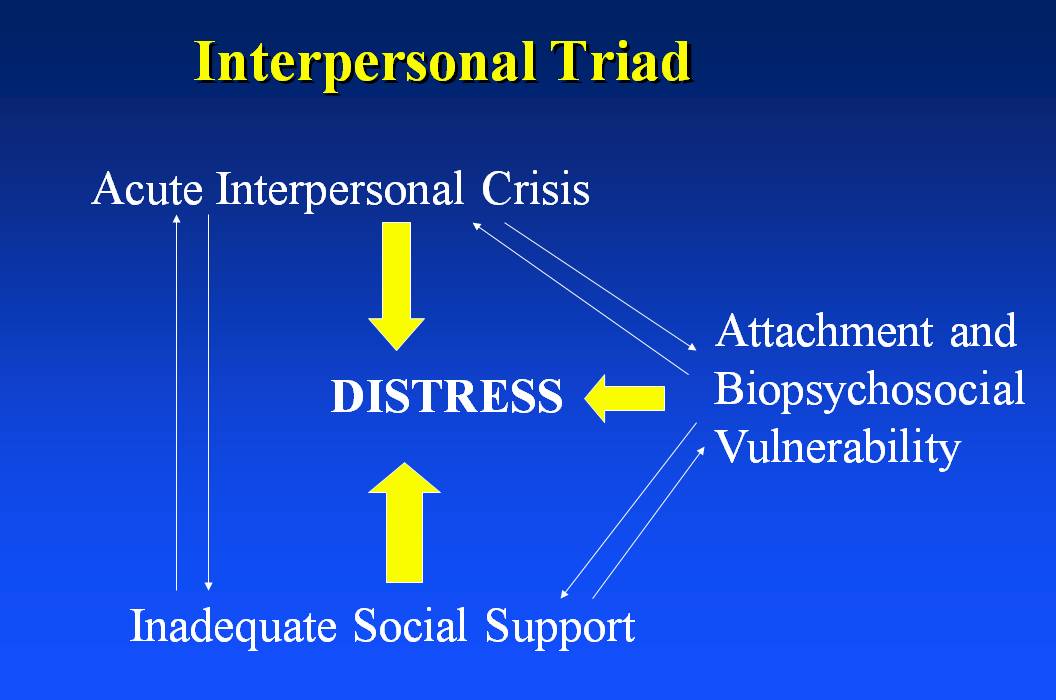
Today's podcast is the second in our four-part series on pathological gambling. I talk with Jody Bechtold, LCSW, NCGC-II, PC about treatment basics for clinicians who work with pathological gamblers. We'll start with a quick overview of crisis intervention and then move into some of the assumptions and techniques of the treatments with the most empirical support in the treatment of pathological gamblers - behavior and cognitive therapy. We end with a brief overview of some challenges that can arise during the treatment of pathological gambling.


This interview targets practicing clinicians or students in clinical courses. If you are not familiar with the approaches discussed in this podcast, you can find more general overviews of crisis intervention, behavior therapy and cognitive-behavioral therapy on the Social Work Podcast website. Disclaimer - this podcast is intended to be a general overview of treatment approaches, rather than a clinical training. If you are currently working with, or intend to work with people with gambling addiction, proper education and training is essential. In the fourth part of this series, Jody and I talk about some of the requirements for obtaining the NCGC-1 - the national certified gambling counselor certification. 


Download MP3 [27:00]

This series on pathological gambling includes the following podcasts:
  1. What is Pathological Gambling? [11:43]
  2. Treatment of Pathological Gambling [27:00]
  3. Thinking Like a Pathological Gambler: Illusions of Control / Chance vs. Skill [8:54]
  4. How to Become a Nationally Certified Gambling Addictions Counselor [27:53]
Update 

References


APA (6th edition) reference for this podcast:

Singer, J. B. (Host). (2007, May 28). Treatment of pathological gambling [Episode 18]. Social Work Podcast. Podcast retrieved Month Day, Year, from http://socialworkpodcast.com/2007/05/treatment-of-pathological-gambling.html

Tuesday, May 22, 2007

What is Pathological Gambling?

Today's podcast is the first in our four-part series looking at the DSM-IV-TR diagnosis of pathological gambling. In today's podcast, Jody Bechtold, LCSW, NCGC-II, PC looks at what it is, what it is not, and what are the similarities and differences between pathological gambling and substance use disorders.


Download MP3 [11:43]

Music: Money by Pink Floyd; Viva Las Vegas by Elvis, and Luck be a Lady by Frank Sinatra.

This series on pathological gambling includes the following podcasts:

  1. What is Pathological Gambling? [11:43]
  2. Treatment of Pathological Gambling [27:00]
  3. Thinking Like a Pathological Gambler: Illusions of Control / Chance vs. Skill [8:54]
  4. How to Become a Nationally Certified Gambling Addictions Counselor [27:53]
Updates:

APA (6th edition) reference for this podcast:

Singer, J. B. (Host). (2007, May 22). What is pathological gambling? [Episode 17]. Social Work Podcast. Podcast retrieved Month Day, Year, from http://socialworkpodcast.com/2007/05/what-is-pathological-gambling.html

Thursday, April 19, 2007

Interview with Dr. Edward Sites: Women in Social Work

In today’s podcast, I talk with Dr. Edward Sites about women in social work. Dr. Sites gives us a historical perspective of the role of women who were born at or before 1900 in the development of social work as a profession in the United States.

Dr. Edward Sites, Ph.D., ACSW, LCSW, BCD, has devoted his entire career of nearly 50 years to child welfare practice, education and research, the last 41 years of which have been as a faculty member at the University of Pittsburgh School of Social Work where Dr. Sites was a full professor from 1978 until his retirement in 2006. He is the longest serving School of Social Work faculty member in the School’s 70 year history. At his retirement, he was the principal investigator of 9 projects and programs with total annual budgets of over $30 million and a state-wide staff of nearly 100 faculty and professional staff. These projects included research, degree and training programs in collaboration with 16 universities, and provided over 35,000 days of training annually to 4,000 public child welfare employees and 9,000 foster parents in all of Pennsylvania’s 67 counties as well as baccalaureate and master’s degree programs for hundreds of child welfare workers annually. Dr. Sites has received a number of prestigious awards including NASW Social Worker of the Year in Pennsylvania (1996); the Bertha Paulssen Medal (2001); the Chancellor’s Distinguished Public Service Award from the University of Pittsburgh (2003), and the Distinguished Alumni Award from the School of Social Work at the University of Pittsburgh (2004).


Download MP3 [49:24]

Recent publications

  • Cahalane, Helen and Sites, Edward W. (2008). The climate of child welfare employee retention. Child Welfare, 87, 91-114
  • Friedman, M.S., Koeske, G.F., Silvestre, A.J. Korr, W. S, and Sites, E. W. (2006). The impact of gender-role nonconforming behavior, bullying and social support on suicidality among gay male youth. Journal of Adolescent Health, 28(5), 621-623.
  • Sites, Edward W. (2005). Child Welfare in the 21st Century: A Commentary. Journal of Children and Poverty, 11(2), pp. 169-175.
  • Newhill, Christina E. and Sites, Edward W. (2005). Identifying Human Remains Following an Air Disaster: The Role of Social Work. In Turner, Francis J. (Editor) Social Work Diagnosis in Contemporary Practice. New York: Oxford University Press.
  • Sites, Edward W. (2001). Paulssen Power. Seminary Ridge Review, 3(2), 31-37.
  • Newhill, Christina E. and Sites, Edward W. (2000). Identifying Human Remains Following an Air Disaster: The Role of Social Work. Social Work in Health Care, 31(4), 85-105. 

References

  • National Conference of Charities and Correction. (1910 - 1914). Proceedings of the National Conference of Charities and Correction. (Alexander Johnson, Editor). Fort Wayne: The Archer Printing Company.
  • National Conference of Charities and Correction. (1935). Proceedings of the National Conference of Social Work: Index 1874-1933. Chicago: University of Chicago Press.
  • National Association of Social Workers. (1995). Encyclopedia of Social Work, Vol. 3. (R. L. Edwards, Editor) Washington: NASW Press.


APA (5th edition) reference for this podcast:

Singer, J. B. (Host). (2007, April 19). Interview with Dr. Edward Sites: Women in social work [Episode 16]. Social Work Podcast. Podcast retrieved Month Day, Year, from http://socialworkpodcast.com/2007/04/interview-with-dr-edward-sites-women-in.html

Monday, March 26, 2007

Reality Therapy

In today’s podcast we will look at Reality Therapy, developed by Dr. William Glasser. We briefly review the assumptions of choice theory and how those assumptions are translated into Reality Therapy. The majority of today’s short podcast comes from the Gerald Corey text, Theory and Practice of Counseling and Psychotherapy

Download MP3 [18:19]


Transcript

Hello and welcome.  You found The Social Work Podcast.  My name is Jonathan Singer and I'll be your host as we explore all things social work.
 
Today we're talking about reality therapy.  Reality therapy was developed by Dr. William Glasser.  Like Carl Rogers, developer of person-centered therapy, Albert Ellis and Aaron Beck, both of whom developed cognitive behavioral therapies, Glasser started his career as a psychoanalyst but quickly became convinced that the psychoanalytic emphasis on symptoms, childhood experiences and unconscious content actually worked against the change that psychoanalysts were trying to make with their clients.
 
Glasser came to believe that rather than being driven by unconscious choices, our situations were largely the product of conscious choice.  Although reality therapy was originally not associated with the theory, Glasser recognized that control theory provided a congruent theoretical basis for his approach to treatment.  After two decades of modifying control theory, Glasser believed that his theoretical basis was sufficiently different to rename control theory into choice theory.
 
These days reality therapy is grounded in Glasser’s choice theory and clinicians are taught choice theory as a part of their training to become certified reality therapists.  In today’s podcast, we'll briefly review the assumptions of choice theory and look at how they're applied in reality therapy.  Now one disclaimer, I'm not a certified reality therapist.  Most of the information that I've gathered for this lecture comes from Gerald Corey’s chapter on reality therapy in the 7th Edition of his text Theory and Practice of Counseling in Psychotherapy.
 
Choice theory states that people choose their behaviors and that these choices are made to satisfy five basic needs: survival, love and belonging, power, freedom and fun.  Now just as a side note, it's not often that you find a theoretical model that assumes that fun is a basic need.  So right off the bat, reality therapy has something going for it that almost no other therapy model has.  Now the most important of these basic needs is love and belonging.  Love and belonging are the most important needs because they're the basis for forming relationships and relationships are the core of satisfying the other needs.
 
So let's take a brief look at the five basic areas of survival, belonging, power or achievement, freedom or independence and fun or enjoyment.  One way of getting to this issue of survival, this basic need of survival is you can ask yourself to what degree are you maintaining vitality and good health rather than merely surviving.  In order to get at the basic need of belonging, you can ask in what ways do you feel a sense of belonging or what do you do to meet your needs for meaningful relationships.
 
In terms of power or achievement, you can ask when do you feel a sense of power, in what areas of your life are you making significant achievements and when do you feel recognized by others.  For freedom or independence, you can ask to what degree do you feel that you were in charge of your life and are moving in the direction that you want.  And finally for fun or enjoyment, you can ask what are those activities that you do for fun and do you have as much fun as you would like.
 
If you go see a reality therapist, it's likely that he or she will assume that the underlying problem is either that your relationships are unsatisfying or that in fact you lack relationships to begin with?  The basic goal of treatment would be to help you develop behaviors that result in new or behaviors that improve existing connections with others.  Because of this emphasis on relationships, the reality therapist uses the client-therapist relationship as a model for developing satisfying connections with others.
 
The therapist will work very hard to keep the focus on the present.  And this serves two purposes:  First, it keeps you focused on the choices that you're making moment to moment to satisfy your basic needs.  And second, it reinforces the importance of relationships in ultimate happiness.  So how come it is that we make choices that end up hurting us.  Wouldn’t it make sense that we would choose behaviors that would get us what we want?  Why would we intentionally choose behaviors that would make us miserable instead of making us happy?
 
Well, Glasser would say that in fact we mistakenly choose misery in our best attempts to meet our needs.  This mistake is caused by a gap in what we really want and what we think or perceive that we want.  See, we have an ideal world referred to in choice theory as a quality world that reflects what we want.  We often confuse what we want with what we need.  In doing so, we confuse our ideal world with reality.  For example, I don’t need that second piece of cake.  If I tell myself that I need it then I'll choose behaviors that will help me satisfy that need even if those behaviors will ultimately end up in me feeling worse not better.
 
If however I tell myself that I want a piece of cake then I acknowledge that having that second piece is a choice.  Now, getting a second piece of cake is pretty tame.  Confusing the want of cake with the need of cake seems pretty obvious and you wouldn’t imagine that somebody would go in for therapy just for that.  Well, cake can be cake and it be a serious issue for folks with eating disorders, but let's imagine what if instead of cake I told myself that I needed to score some crystal meth or that I needed to revenge the death of my brother.  Well, there's a world of difference between wanting crystal meth and needing crystal meth and wanting to avenge the death of my brother and needing to.
 
You see the difference?  You see the qualitative difference between wanting something and needing something?  When we tell ourselves that we need something, it makes it an imperative.  It says I need this just like I need air, just like I need to breathe, just like I need food to sustain myself.  It's not a want, it's a need and because it's something that is basic to my survival I will stop at nothing to get it.  Well, Glasser would say that in fact most of the things that we think of as needs are in fact wants.  We want these things.  We don’t need them.
 
So, our behaviors are geared towards getting what we want.  In reality therapy, behavior is not just a physical act.  Choice theory says that doing, thinking, feeling and physiology comprise what they call total behavior.  Now doing is active behaviors.  Thinking, those are thoughts and self statements, the things that we tell ourselves like I need that second piece of cake.  That’s a self statement.  Feelings are just what you would think of as feelings, anger, joy, pain, anxiety and physiology is bodily reactions.
 
Ultimately, behavior is purposeful because it is designed to close the gap between what we want and what we perceive we are getting.  So what do these ideas look like in a therapy context?  Well, Gerry Corey illustrates the practice of reality therapy by using the WDEP system developed by Dr. Wubbolding.  So let's take a minute to talk about this approach to reality therapy.
 
The WDEP system, W stands for wants.  What do we want to be and what do we want to do with our lives?  The D stands for doing and direction.  Where are we going?  What are we doing?  The E stands for evaluation.  Does your present behavior have a reasonable chance of getting you what you actually want?  And the P in the WDEP system stands for planning.  And there's a nice little acronym that the good doctor has come up with to help us remember the stages of planning and that’s SAMIC3 or SAMIC.
 
So, S stands for simple.  When you plan something, it has to be simple.  It has to be easy to understand, specific and concrete.  A is attainable and by attainable I mean that whatever it is that you're setting out to do has to be within your capacity and motivation to actually attain.  So you can say that you want to become the president of the United States, but if that’s not within your capacity and you're not motivated to do all that you need to do to become the president then that’s not a reasonably attainable part of your plan.  It has to be measurable.  Are the changes observable and are they helpful?
 
The I in SAMIC stands for immediate and involved.  What can be done today?  What can you do today to make this change?  This idea is really helpful because when you work with a therapy client it's possible that they might not come back for a second session and so the session that you have is the session that you have the opportunity to actually make some differences.  So what is it that your client is doing today?  What is immediate and what is it that you can do to be involved?
 
And the C stands for control.  Can you do this by yourself or will you be dependent on others?  I want to say one thing about this last part.  Being dependent on others does not mean that you are not in relation with others.  Obviously, the core belief in reality therapy is that our problems arise when we are not relationships or relationships are not satisfying.  So it wouldn’t make any sense to have part of the plan for getting us what we want to be in isolation.
 
The C in the SAMIC planning part, can you do this by yourself or will you be dependent on others, refers to this idea that if you are going for something but getting that will ultimately depend on somebody else, it means that you might be setting yourself up for failure.  Take for example a job.  What if you wanted to get a position that was somewhat out of your control, that by doing all that you could do you might still end up not getting this job.
 
And you wouldn’t get this job because it was dependent on somebody else deciding that you were the best person for this job.  Well, having any part of your plan be dependent on somebody else for success is ultimately going to end up in failure.  So the idea is to identify what it is that you can control in terms of this plan.  Remember earlier when we're talking about basic needs, the five basic needs?  Well, the way that it's used in therapy is that you identify what somebody is looking for, what they want, the W in the WDEP model and you ask them to look at an area in their life.
 
It could be what they want from their self, friends, spouses, religion, spirituality, work or the larger world around them and then they select one of these targets for further exploration.  And then you ask three questions of those particular areas.  The first is what are you doing now to get what you say you want?  How much effort are you devoting to getting what you want?  The second question is how do you perceive yourself and significant others in your life? And then finally how are you meeting the basic needs?
 
So, at that point you come into these issues of basic needs and you ask your client to rank their basic needs.  So it could be that for them this issue of belonging, the love and the relationships is the most significant need that they have right now.  Then what you do is you ask them well what are you willing to do to change this aspect of your life and that’s where the reality therapy really starts coming in.  That’s where people get down to brass tacks about what it is that they're doing, the choices they have made, the situation that they have created for themselves and acknowledge that that situation is in part because of their own doing.
 
Now, what's true is that there are some situations where there are things that are somewhat out of our control.  For example, if you are in a job and it is not your choice whether or not you get a promotion then that is out of your control.  However, it could be argued that you have made choices along the way to get yourself in a job where you have less control over your career than if you had been in another job.  So at that point you say well what is it that you're willing to do to change this aspect of your life?
 
Choices aren't necessarily easy nor are they necessarily fun.  But reality therapy would argue that by making choices and being aware of the fact that you have choice that you're that much closer to actually satisfying your basic needs and ultimately feeling fulfilled.  So if we think about some of the strengths of reality therapy, we have to acknowledge that it's a practical approach to identifying what is within the control of the client.  Its focus is on relationships which is a big strength because relationships are universal experience.
 
It has a short-term and focused approach and it works well in many social work settings such as criminal justice, psychiatric hospital, substance abuse and residential treatment centers.  Some of the limitations are that reality therapy really rejects the medical model.  It rejects exploration of the past, of dreams, of dwelling on feelings or insight, transference in the unconscious.  Now, these are limitations only if those things are necessary and are important for your treatment.
 
It also has the limitation of being very direct in terms of questioning and holding people to choices.  And these can be limitations when you're working with culturally diverse clients for whom making the statement “yes I will make this change” is actually incongruent with their cultural upbringing.  So for example, if you ask me as a middle class white male Jonathan, will you do this and I said, “Well yeah, I'll try to do it.” Well, that’s not me making a firm commitment.
 
However, if I was talking to a traditional Japanese father and I said will you do this and he says, “Yes, I will try.” Then culturally that would be the same degree of commitment as for me saying yes, I will do that.  So it's important to take these into consideration.  And finally, as we were alluding to a few minutes ago personal choice is sometimes not a sufficient condition for change in a culture where discrimination and racism are a reality.  So to sum up, reality therapy is a treatment model grounded in choice theory that emphasizes personal responsibility and personal choice.  Responsible behavior enables us to meet our needs without keeping others from meeting their needs.
 
So, I'm Jonathan Singer.  Thanks for being with me today for this episode of The Social Work Podcast.  If you missed an episode, visit our website at https://www.socialworkpodcast.com.  If you have suggestions for future podcasts, please email me.  And to all the social workers out there, keep up the good work.  We'll see you back here next time at The Social Work Podcast.
 
[End of Audio]
(0:18:16)
 

References  

Corey, G. (2005). Theory and practice of counseling and psychotherapy (7th ed). Belmont, CA: Wadsworth/Thomson.  

APA 7th edition

Singer, J. B. (Producer). (2007, March 26). #15 - Reality therapy. Social Work Podcast [Audio podcast]. Retrieved from http://socialworkpodcast.com/2007/03/reality-therapy.html

Monday, March 19, 2007

Cognitive-Behavioral Therapy (CBT)

[Episode 14] In today's podcast, we're going to talk about the therapies that take a cognitive-behavioral approach to working with people. I review the theoretical assumptions, therapeutic process, techniques, use in culturally competent practice, and strengths and limitations of CBT. This podcast is longer than most because I use a lot of clinical examples and dialogue to illustrate the concepts. [Pictured: Tim Beck, developer of CBT, and Albert Ellis, develop of REBT]


Download MP3 [47:11]

Thursday, March 15, 2007

Interview with Kya Conner: Stigma and Social Work

Today we’re going to be talking with Kya Conner about stigma. Kya is a doctoral candidate at the University of Pittsburgh School of Social Work and a masters student in the School of Public Health. She is a Hartford Doctoral Fellow and a CSWE Minority Research Fellow. Kya is also a licensed social worker who maintains a part-time private practice. Her doctoral dissertation is called, Mental health treatment seeking among older adults with depression: The impact of stigma and race. In today’s interview, Kya defines stigma and discusses implications for research, direct practice and public health.


Update: Kya became Dr. Conner on May 29, 2008. Congratulations Kya!

Download MP3 [31:13]


References

Corrigan, P.W. (2004). How stigma interferes with mental health care. American Psychologist, 59(7), 614-625. [PDF]

Corrigan, P.W., & Watson, A.C. (2002). The paradox of self-stigma and mental illness. Clinical psychology: Science and Practice, 9, 35-53.

Corrigan, P. W. & Watson, A. C. (2002). Understanding the impact of stigma on people with mental illness. World Psychiatry, 1(1), 16 - 20. [PubMed article]

Corrigan, P.W. (1998). The impact of stigma on severe mental illness. Cognitive and Behavioral Practice, 5, 201-222.

Goffman, E. (1963) Stigma. Englewood Cliffs, NJ: Prentice Hall.

Jones, E.E., Fraina, A., Hastroff, A.H., Markus, H., Miller, D.T., Scott, R.A., & French, R.S. (1984). Social Stigmas: The Psychology of Marked Relationships. New York : W.H. Freeman & Co.

Link, B.G., & Phelan, J.C. (2001). Conceptualizing stigma. Annual Review of Sociology, 27, 363-385.

Link, B.G., Struening, E.L., Neese-Todd, S., Asmussen, S., & Phelan, J. (2002). Stigma as a barrier to recovery: The consequences of stigma for the self-esteem of people with mental illness. Psychiatric Services, 52, 1621-1626. [PDF]

Ritsher J.B., Otilingam P.G., & Grajales M. (2003). Internalized stigma of mental illness: psychometric properties of a new measure. Psychiatry Research, 121,31-49.

Monday, March 12, 2007

Behavior Therapy

[Episode 12] In this lecture, I focus on the concepts of stimulus and response, rewards and punishments, and how these concepts make operant conditioning such a powerful approach to behavior change. Also in this lecture I touch on classical conditioning, social learning theory and cognitive behavior therapy. The role of the therapist, client, expectations for treatment, implications for multicultural treatment, and the strengths and limitations of the approach are covered.

Download MP3 [41:05]

Thursday, March 1, 2007

Developing Treatment Plans: The Basics

[Episode 11] In this podcast I cover the basics of problem definition, developing goals and measureable objectives as well as identifying interventions and strategies. The key to good treatment planning is making sure that there is a clear and logical relationship between your assessment, problem formulation, goals, objectives and interventions.
Download MP3 [16:34]


Transcript

Monday, February 26, 2007

Interpersonal Psychotherapy (IPT)

[Episode 10] In today's lecture I will will focus on some of the key concepts of IPT, the role of the therapist and client, the structure and goals of IPT - specifically focusing on grief, interpersonal role dispute, role transition and interpersonal deficits, and some of the techniques used in IPT. I'll end with a brief discussion of the applications of IPT, its strengths and limitations.

IPT is a time-limited psychotherapy that was developed in the 1970s and 80s as an outpatient treatment for adults who were diagnosed with moderate or severe non-psychotic, unipolar depression. Over the last 30 years, a number of empirical studies have demonstrated the efficacy of IPT in the treatment of depression. Although originally developed as an individual therapy for adults, IPT has been modified for use with adolescents and older adults, dysthymia, bipolar disorder, bulimia, anxiety disorders and couples counseling. IPT has its roots in psychodynamic theory, but differs from the latter in that it focuses on improving interpersonal functioning in the present. It is similar to CBT in its time-limited approach, structured interviews and assessment tools, but also differs from CBT in that it focuses on the client's affect, rather than cognitions, and the development of a more supportive social network. And whereas nearly all CBTs use homework as a standard part of treatment, although Brief ITP (ITP-B) uses homework, regular IPT may not.

Monday, February 19, 2007

Gestalt Therapy

[Episode 9] Today we're going to talk about the Gestalt therapy, which is part of the existential-phenomenological tradition. The Gestalt approach can be best summed up by the phrase, “the most important moment in a persons life is right now.” Gestalt is an experiential therapy that uses experiments and specific techniques to bring the client into the here and now. Through the experience of the here and now, the client is able to make contact with their environment. Contact is a fleeting experience, but it is during contact that we are in the here and now, and thus are in the process of self-actualizing. During the process of self-actualization we are able to make changes. In today's lecture I will will focus on some of the key concepts of Gestalt, the role of the therapist, the client’s experience and some of the innovative techniques attributed to Gestalt therapy. I’ll end with a brief discussion of the applications of Gestalt, the contributions and limitations of the approach.

Download MP3 [33:44]


References

Burke, J. F. (1989). Contemporary approaches to psychotherapy & counseling: The self-regulation and maturity model. Belmont, CA: Wadsworth Press.

Corey, G. (2005). Theory and practice of counseling and psychotherapy (7th ed). Belmont, CA: Wadsworth/Thomson.


APA (6th ed) citation for this podcast:

Singer, J. B. (Host). (2007, February 19). Gestalt Therapy [Episode 9]. Social Work Podcast. Podcast retrieved Month Day, Year, from http://www.socialworkpodcast.com/2007/02/gestalt-therapy.html

Monday, February 12, 2007

Person-Centered Therapy

[Episode 8] Today we're going to talk about Carl Rogers and his revolutionary approach to psychotherapy - Person-Centered Therapy. Next to Freud, no other therapist has influenced the practice of therapy more than Carl Rogers. The humanistic assumptions at the core of Person-Centered therapy stand in stark contrast to the problem-centered, expert-oriented approach of what was then the dominant model of psychotherapy - Freudian Psychoanalysis. Rogers gave us an equation that would forever change the concept of therapy...

Existential Therapy

[Episode 7] In today's podcast, I talk about Existential therapy as an intellectual or philosophical approach to working with people. Although some authors have attempted to manualize Existential therapy (see Keshen, A. (2006). A new look at existential psychotherapy. American Journal of Psychotherapy, 60(3), 285-298), the existential approach is not known for specific techniques or procedures. Rather, its influence has been most notable in encouraging clinicians to focus on the ideas of freedom of choice, the responsibility that accompanies choice, and the notion that the inevitability of death is what gives life meaning.


Download MP3 [18:09]


Transcript

Today, we're going to be talking about existential therapy.  Existential therapy is an insight-oriented therapy much like Freudian psychoanalysis or Adlerian personal psychology.  What distinguishes existential therapy from other insight-oriented therapies is that existential therapy is more of a philosophical or intellectual approach to understanding a person’s problems rather than a set of techniques.  Existential therapy emphasizes our freedom to choose what we make of our circumstances and believes that we are free and therefore responsible for our choices and actions.

In essence, as Gerald Corey (2005) writes, we are the authors of our lives. Gerald Corey identifies six key concepts associated with existential therapy.  The first is that we have the capacity for self awareness.  Now, the greater our awareness, the greater our responsibilities for freedom and Corey writes that awareness is realizing that we are finite, that we understand that time is limited.  We have the potential and the choice to act or not to act and that meaning is not automatic that we must seek it.  And finally, that we are subject to loneliness, meaninglessness, emptiness, guilt and isolation.

The second key concept is that because we're basically free beings, we must accept the responsibility that accompanies our freedom.  In other words, because we're free to choose we have to take responsibility for the choices that we make.

A third key concept is that we have a concern to preserve our uniqueness and identity.  We come to know ourselves in relation to knowing and interacting with others.  Our identity is the courage to be.  We must trust ourselves to search within and find our own answers. Corey writes that one of our greatest fears is that we'll discover that there is no core and no self.  Another key concept is that the significance of our existence and the meaning of our life are never fixed once and for all.  Instead, we recreate ourselves through our projects.  Our search for meaning must be pursued obliquely.  This means that finding meaning in life is by necessity a by-product of a commitment that we make to creating, loving and working.

Another way of thinking about this is that we can't directly seek meaning.  Rather, we have to engage in activities and it is through that engagement that we actually find the meaning in our lives.  Viktor Frankl talked about the will to meaning as our primary focus in life.  Frankl said that life in and of itself is not meaningful. The individual must create and discover that meaning.

Now, one of the themes here is that people are creating their own realities and this is a phenomenological approach similar to Adler but very dissimilar to Freud and this phenomenological approach assumes that we are actively involved in the creation of our own realities.  As a therapist, if we understand that our client is creating their own reality, it's therefore important for us to assess and identify what that reality is and the meanings that our client is making of his or her reality.

Final key concepts include anxiety as part of the human condition.  The existentialist believes that anxiety is a basic condition of life and they call this existential anxiety and they consider it to be normal.  In fact, life can't be lived nor can death be faced without anxiety.  Anxiety can be a stimulus for growth as we become aware of and accept our freedom.  We can blunt our anxiety by creating the illusion that there is security in life and if we have the courage to face ourselves in life, we might be frightened, but we will be able to change.

A final concept is that death is a basic human condition and awareness of death gives significance to living.  So, these are the six key concepts that Corey identifies in existential therapy.

One of the criticisms of existential therapy is that its concepts can be vague and hard to understand, so in the attempt to make it a little bit more clear what existentialist stand for I'm going to compare and contrast the existential approach to therapy with Freud’s psychodynamic approach.

Existentialism believes that we are free to make our choices and we're not hindered by the past or by biological drives.  In contrast, Freudian psychoanalysis believes that freedom is restricted by unconscious forces, irrational drives and past events.  In existentialism, anxiety can be useful.  In psychodynamic theory, anxiety or neurosis is not useful and is in fact pathological and something that needs to be addressed.

In existentialist therapy, techniques are antithetical to truly being there for the client.  This is one of the reasons why existential therapy is more of an approach rather than a prescription for therapy.  In Freudian psychoanalysis, techniques are essential to making the unconscious conscious and these techniques can include dream analysis, transference, counter-transference, interpretation, very specific things and it's specific because the therapist is considered the expert in interpretation and understanding the objective world of the client.

Now both existential and psychodynamic are insight orient.  In existential therapy, treatment is based on the here and now and explorations of the past seek to identify the origins of the world view.  Again, there we have this idea that our clients are constantly creating the way that they understand the world, so explorations of the past are simply a way of better understanding how our clients came to view the world that they do.

In psychodynamic therapy, change occurs by exploring the past.  In existential treatment, dream analysis sheds light on possibilities.  Dreams are commonly understood to mean I don’t know what's happening to me.  In contrast in Freudian psychoanalysis, dream analysis identifies unconscious content that symbolizes conscious issues.  This is a very different approach because again you have symbols that have objective meanings in psychodynamic frameworks
such as a cigar is sometimes not a cigar.

In contrast in existential therapy, dreams are seen more as close as to the meaning that people have made for themselves.  So, one clarifying example is that if we imagine that we're working with a war vet and the vet meets criteria for posttraumatic stress disorder, is having difficulty focusing on family relations, difficulty holding a job, has exaggerated sterile response, is increasingly focused on issues related to current conflicts around the world as presented on the TV and radio.

Psychoanalysis might say that the war experiences have triggered repressed pre-sexual experiences for the vet and that the impulses are in conflict with the super ego.  In contrast, in existential approach to therapy, you must say that without the focus on the Vietnam and posttraumatic symptomology, the vet’s world would be revealed as pointless and absurd.  If there were specific issues around building a family or future orientation that the vet was having a hard time addressing, existential therapy would probably say this is because the vet is not considering the future as viable and instead understanding that the imminence of death is causing serious questions as to the point of life.

Now, the therapist-client relationship is considered to be collaborative.  In fact, Corey describes it as a journey taken by the therapist and the client together.  The relationship demands that the therapist be in contact with his or her own phenomenological world.  That is, the therapist must be aware of the way that he or she is constructing their own world so that they understand that their client is constructing his or her own world and that those worlds are necessarily going to be somewhat different.

The core of the therapeutic relationship is respect and faith and the client’s potential to cope and sharing reactions with genuine concern and empathy.  Now, some therapeutic goals in existential therapy include giving attention to the client’s immediate ongoing experience with the aim of helping them to develop a greater presence in their quest for meaning and purpose.

Another goal is to recognize factors that block freedom.  A third goal is to challenge clients to recognize that they are doing something that they formally thought was happening to them.  So, again, this addresses the concept of freedom and responsibility.  If your client believes that child protective services is something that is happening to them, it's important for you to help them understand that in fact they are active participants in this world in this situation and that their choices and their decisions are components of the current situation that they're in.

No judgment on whether or not a confirmed case of abuse has merit, but I'm just saying that in existential theory that the important thing is to focus on helping your client understand their own action as being part of their world.  And finally, the goal – the final goal is to accept freedom and responsibilities that go along with that action.

The phases of counseling can be broken down into the initial, the middle and final.

In the initial phase, you really want to see how your client understands their world. Again, this is the phenomenological viewpoint.  In the middle phase, you can explore how your clients develop that view of the world and how that view of the world is affecting what's currently going on with them, how that emphasize or how that influences what it is that they see as their responsibilities, their actions, what they have choices over.  And finally, the last phase of counseling is geared towards understanding how clients can take what they’ve learned in making their lives more purposeful, intentional and grounded in meaning.

Some of the things to do during the assessment phase is to identify existential themes and these are themes related to responsibility, mortality, isolation and meaningless.  These are the big four that Yalom discussed in his classic 1980s text “dreaming like waking is a mode of existence or being in the world and special attention is paid to themes and dreams in making sure not to place emphasis on the therapist’s interpretation.”

So whereas in Freudian psychoanalysis, really it's the therapist that’s responsible for ultimately interpreting what a dream means not because the client is unconscious of the meaning.  In existential approaches, it's really the client that ultimately determines what a dream means.  Some assessment techniques are the use of objective and projective tests such as the Rorschach and the thematic apperception test, the purpose of life test.  This addresses individuals’ views of life goals, their world and their death and the experiencing scale which looks at feelings and self-awareness.

Because there are no specific techniques in existential therapy, application really looks like incorporating techniques and approaches that you as a therapist are comfortable using.  Just remember that as you use your techniques, the primary emphasis is on understanding the client’s current experience.  As you adapt interventions that you're really focusing on these issues of choice, freedom and responsibility and ultimately you're guided by the philosophical framework about what it means to be human.

Now, existential therapy has been applied to multiple areas.  Clients who are seeking personal growth are great candidates for taking an existential approach, career or marital failure, retirement, grief work and any transition from one stage of life to another.  Existential approaches are wonderful for working with teenagers and for whom the questions of what is my purpose, what is the meaning of my life, how am I to live the best life I can, all of these questions are classic teenage angst questions.

A final area of application is helping those who are struggling to find meaning in life and facing the anxiety of their eventual death.  An obvious group for this is older adults.  Existentialist philosophy and existential therapy have contributed a lot to social work practice and clinical work in general.  One of the big ones is that existential theory contributed the concepts of self-determination and personal responsibility.  It provided a perspective for understanding the value of anxiety and guilt and the role and meaning of death in treatment.

The existential approach really enables clients to examine the degree to which their behavior is influenced by social and cultural conditioning.  In his 2005 text, Gerald Corey in fact argues that the existentialist approach is perhaps the most culturally competent approach because it provides social workers with a framework for understanding the universal issues of freedom, choice, life and death and because it's not technique-bound there are no cultural limitations on how this approach is practiced.

However, one of the limitations of an existentialist approach is that it lacks systematic statements of principles and practices of therapy.  It uses vague and global terms and abstract concepts that can be very difficult to grasp such as the will to meaning.  Finally, it's not been subjected to scientific research as a way of validating its procedures.

Now, in a recent article, Aaron Keshen acknowledged the limitations of existential therapy primarily in its lack of empirically testable techniques or approaches.  In a 2006 article, he attempts to operationalize existential techniques.  If you want more information on his approach, his article can be found in the American Journal of Psychotherapy, volume 60, issue 3 and the article is called “A New Look at Existential Psychotherapy” and in this article he attempts to operationalize the issues of your actual purpose or your substituted purpose in life and then he applies those to issues of mental illness, substance abuse, personality disorders, things like that.


So, in conclusion, existential therapy is really a philosophical or intellectual approach that provides the therapist with a framework to understanding their client’s problems rather than providing a set of techniques for actually addressing the problems the clients come in with.  The main issues that existential approaches address are issues of freedom, the freedoms that we have to choose and the responsibilities that come with those choices.  The other main issues that are significant are issues of the meaning of life and the reality and acceptance of death.


References


Burke, J. F. (1989). Contemporary approaches to psychotherapy & counseling: The self-regulation and maturity model. Belmont, CA: Wadsworth Press.

Corey, G. (2016). Theory and practice of counseling and psychotherapy (10th ed). Belmont, CA: Wadsworth/Thomson.

Keshen, A. (2006). A new look at existential psychotherapy. American Journal of Psychotherapy, 60(3), 285-298.


APA (6th ed) citation for this podcast:

Singer, J. B. (Producer). (2007, February 12). Existential therapy [Episode 7]. Social Work Podcast [Audio podcast]. Retrieved from http://socialworkpodcast.com/2007/02/existential-therapy.html

Monday, February 5, 2007

Adlerian Psychotherapy

[Episode 6] In this lecture, I discuss key elements of Adler's Personal psychology and how this approach contrasts with Freud's theory. The contrast between Adler's and Freud's approaches can best be summed up in the quote "We are pulled by our goals, rather than pushed by our drives."

Download MP3 [15:02]


References


Burke, J. F. (1989). Contemporary approaches to psychotherapy & counseling: The self-regulation and maturity model. Belmont, CA: Wadsworth Press.

Corey, G. (2016). Theory and practice of counseling and psychotherapy (10th ed). Belmont, CA: Wadsworth/Thomson.

Rychlak, J. F. (1981). Introduction to personality and psychotherapy (2nd ed.). Boston: Houghton Mifflin Company.


APA (6th ed) citation for this podcast:

Singer, J. B. (Producer). (2007, February 5). Adlerian psychoanalysis [Episode 6]. Social Work Podcast [Audio podcast]. Retrieved from http://socialworkpodcast.com/2007/02/adlerian-psychotherapy.html

Freudian Psychoanalysis

[Episode 5] In this lecture, I discuss key elements of Freud's theory of personality and how that translated into his approach to therapy. The central goal of Freudian psychoanalysis is to make the unconscious conscious.

Transcript

[0:00:13]

In today’s podcast, we're looking at two of the major figures in psychodynamic therapy:  Sigmund Freud and Alfred Adler. Sigmund Freud, of course, the father of psychoanalysis and Alfred Adler, developer of individual psychology. These two men had a lot in common, as did their approaches to therapy. In fact, the most common element to their therapies is that they were insight-oriented. These men believed that insight into why you do things is actually the key to making changes and living a happier, more successful life.  The way that these men conceptualize change was very different and that’s what we'll be talking about in today’s podcast.

In Freudian psychoanalysis, which is also called Id Psychology, the goal of treatment is to make the unconscious conscious. For example, let's say you're working with a man who has a confirmed case of physical abuse against his children. His explanation as to why he beat his children is that they deserved it. However, during your treatment you discovered that this man hates his boss. He also hates his abusive father. It becomes clear that his boss reminds him of his abusive father.

But your client was unaware of this connection. That is, he was not conscious of the connection between his emotions towards his father and his boss. Although his boss certainly has some characteristics of his father, you're able to point out to him that he’s employing a defense mechanism called displacement, where he is redirecting his feelings about his father to his boss. However, because he cannot act out his aggression towards his boss for fear of losing his job, he then displaces his anger on his children.

Freud would say that he is displacing his anger as a way of protecting himself, ultimately against addressing his deep-seated anger towards his father. In this example, by making your client aware of his unconscious anger, he’s able to gain insight into his behaviors and thereby he’s able to make not only situation-specific changes, but more importantly, changes in his personality. Now, this concept is key in understanding Freudian psychoanalysis.

Without a belief in the existence of an unconscious, Freud’s techniques and his approaches to treatment really make no sense. So, we're going to start out by talking about the topographical model: that is the conscious, the pre-conscious and the unconscious. Freud believed that the mind was divided into three layers.

You have the conscious layer, which was just a thin sliver on top and these were thoughts and ideas that we're aware of. So for example, if you ask me for a telephone number and I'm able to bring it up and say: “Oh yeah, the telephone number is 555-1212.” That telephone number is in my conscious. If you ask me for a phone number and then I have to think about it for a little bit, but I eventually come up with it, then Freud would have said that that phone number was in my pre-conscious (that was somewhere in between the conscious and the unconscious). I knew that it was pre-conscious and not unconscious because I was consciously able to recall it.

Information or data that we’re consciously able to recall can't be unconscious in Freud’s structure. By unconscious, I mean that these are things we're not aware of, also known as repressed material. The clinical evidence that Freud used for postulating the existence of the unconscious included: dreams, slips of the tongue, post-hypnotic suggestion, material derived from free association, material derived from projective techniques (such as ink blots, Rorscharch’s, things like that) and the symbolic content of psychiatric symptoms.

In Freudian theory, personality development hinges on the successful resolution of each phase of development. Erikson shares this concept with Freud, but for Freud it is psychosexual development and particularly inadequate resolution of a particular phase of psychosexual development can lead to neurotic behaviors, such as phobias. Now, in adulthood, the inadequate resolution of particular [00:05:00] phases is directly linked to unconscious wishes and impulses that seek to satisfy conflicting internal drives.

The structure of the personality, as it develops, starts out with the id. The id is the demanding child and is ruled by the pleasure principle. An easy way to think about the id is to think of a 1-year-old, somebody in the oral stage. That child is ruled entirely by: what feels good, what's going to soothe it, what's going to make it full, what's going to allow it to go to sleep, what's going to calm it. The 1-year-old child doesn’t think too much about: "Well, maybe I should give mom a break because I kept her up all night screaming."

The 1-year-old child is interested in getting fed when he wants to get fed or going to the bathroom when she wants to go to the bathroom. So people who are ruled by pleasure principles are considered to be dominated by the id. That is their personality is dominated by the id. In contrast to the id, the super ego is the judge and this is the part of our personality that’s ruled by the moral principle. The moral principle is: do what's right.  And the moral principle isn't necessarily good for us.

That is if we rule (if we lived entirely by the moral principle), then we wouldn’t necessarily be any better off than somebody who lives entirely by the id or the pleasure principle. So in order to have a balance between the id and the super ego, Freud postulates that there is the ego (sometimes thought of as a traffic cop) and the ego is ruled by the reality principle. This is where the ego takes into consideration some of the pleasure principle, some of the impulses of the id as well as some of the ideas of what's just and moral (imposed by the super ego) and then takes all that information into consideration and compares it to what is necessary in this situation in a realistic manner.

So it's not realistic to do everything you want all the time nor is it realistic to act god-like. We have to be real and that’s how we connect with other people. Now, ego defense mechanisms are defense mechanisms that are used by the ego. They're normal behaviors, which operate on an unconscious level, which tend to deny or distort reality. These defense mechanisms help individuals cope with anxiety and they prevent the ego from being overwhelmed.

So for example, denial is a classic defense mechanism. Denial is when the ego says: “No, that didn’t really happen.” Then you have the most fundamental defense mechanism of repression. And repression is literally when material is pushed into the unconscious so that we're not even aware of it. Now, it's common for people to say: “Oh, I totally repressed that.” But that’s actually an inaccurate use of the Freudian concept of repression. If we're conscious of repressing something, then it can't be unconscious. Instead what we're actually talking about is suppression: “I suppressed the memories of the party from the other night.” That would be suppression.

Finally, ego defense mechanisms can have adaptive value if they do not become a style of life to avoid facing reality. The therapeutic goals for Freudian psychoanalysis are to make unconscious motives conscious, because only then can an individual exercise choice. And when that happens, this ego can be strengthened so that behavior is based more on reality and less on instinctual cravings (that will be the id) or irrational guilt (which would be the super ego).

Essentially, psychoanalytic treatment revolves around uncovering and interpreting unconscious impulses and defending against them. Now Freud is famous for his psychoanalytic techniques and the reason why these techniques are so important is that in psychoanalysis the therapist, [00:10:00] the analyst, is the expert. The analyst is the expert in interpreting the material that the client brings up. And the reason why the analyst has to be the expert is because by theory the client is not aware of what it is that they're doing.

So for example, if I'm sitting in my therapist’s office and I'm free associating (which is one of Freud’s famous psychoanalytic techniques) and I'm talking about my work and I list a whole string of words that I associate with work and a whole bunch of ideas, I'm not necessarily going to be able to identify what unconscious material is being brought up. It is up to the therapist to say: “Uh-huh, it seems like this is what's going on.” And that’s the interpretation piece of psychoanalysis.

For this reason, classically trained psychoanalytic therapists had to go through their own psychoanalysis. So some of these psychoanalytic techniques include free association, (which I was just talking about) and this is when the client reports immediately without censoring any feelings or thoughts. Another technique is interpretation. In an interpretation, the therapist points out, explains and teaches the meanings of whatever is revealed.

Now Freud believes that we can only get in touch with the unconscious by interpreting what it seems to be indicating in our dreams, waking fantasies, slips of the tongue and so on. Freud believed that you could communicate on two levels at the same time, the conscious and the unconscious. For example, if you're having a professional conversation (that would be a conscious act) and engaging in intimate body language (that could be unconscious flirting) then you're accessing both your conscious and your unconscious simultaneously and only a trained psychoanalyst could point out what the unconscious material is. That’s why the traditional therapeutic relationship had to be expert-driven rather than collaborative.

A third psychoanalytic technique is dream analysis and dream analysis is called “the royal road to the unconscious.” During your dreams: images appear, ideas, scenes out of a movie will pop up in your head. And Freud believed that these were not realistic in the sense that, if I'm driving a car, it doesn’t actually just mean that I'm driving a car. There is important information in these images that are symbolic of something that’s going on in my unconscious.

Freud also believed that certain symbols were universal. For example, bodies of water always represented the unconscious in Freudian theory. So, if I was floating on a lake, I would be floating on my unconscious and that lake could be calm or it could be choppy and these would mean things in Freudian psychoanalysis.

Now transference is when the client reacts to the therapist as she does to an earlier significant other. Transference allows the client to experience feelings that would otherwise be inaccessible. In the analysis of transference, the therapist is able to achieve insight into the influence of the client’s past.

Countertransference is the reaction of the therapist towards the client that may interfere with objectivity. And remember in Freudian psychoanalysis, the analyst is considered to be a blank slate and objective, so these ideas of transference and countertransference are really key and very important. And I believe that these are two of the concepts that are actually most useful to draw on from traditional Freudian psychoanalysis.

For example, if you're working with the client and they start to talk to you as if you are their father or you are their grandson or possibly you are their girlfriend, they're somebody other than who you are, then Freud would say that they are transferring unconscious material onto [00:15:00] you.

Now one easy explanation for why this happens is because most of the time therapists do not spend a lot of time talking about themselves, in their lives, in the therapy room and so clients have to do something. They have to create some image of the therapist and when this happens, oftentimes they project information from their own lives. Now, this can be really useful if you're working with, say a woman who’s been in an abusive relationship, and she starts to interact with you as if you are an abuser. Now assuming that you're an ethical clinician and you are in fact not abusive, you can use this material to work in the moment with the client about these feelings and really work on these issues in a here and now way.

Although this isn't traditionally psychoanalytic, it is a modern adaptation of the concept of transference. If however, you're working in a session with a client and you find yourself looking at her as if she’s your daughter or perhaps your mother or even possibly if she were your lover, then that could suggest countertransference, reactions that you're having towards your client. And unless you're aware of these and are dealing with these actively, they can certainly interfere with your ability to provide a professional service to your client.

The last psychoanalytic technique that I'll talk about is resistance; and this is anything that works against the progress of therapy and prevents the production of unconscious material. These days in social work we don’t necessarily think of clients as being resistant. Resistant clients were traditionally conceptualized as clients who are actively trying to sabotage treatment. Today, if a client says: “That treatment is not working for me “or “I don’t want to do that,” we first look to ourselves and find out if we're doing a poor job of treatment matching for our clients.

The assumption is that if we find the right thing, if we've done our job at collaborating with our clients on identifying goals and developing treatment plans, then our clients will actually engage in the treatment, rather than saying that they don’t want to do it. In contemporary psychoanalysis, the relationship tends to be collaborative and although problems are grounded in the past, the focus is on alleviating current problems. Contemporary psychoanalysis also incorporates modern therapy techniques.

A modern day adaptation of Freud’s individual psychoanalytic therapy is psychoanalytic family therapy. Rather than emphasizing instincts and drives, the focus is on attachment objects and their role in individuation and personal growth. Now, the contributions of Freudian psychoanalysis are almost immeasurable. The concepts and ideas are so interwoven into our everyday lives that it's hard to really distinguish what is psychoanalytic and what is just the way we think about things.

For example, it's not uncommon to hear somebody complaining of somebody having an anal personality. It's also not uncommon to hear jokes that refer to some of the core concepts that Freud developed, as in this joke about Freudian slips. This joke was told to me by a British friend of mine:

Patience says to his doctor: “Doctor, I had a Freudian slip last night. I was eating dinner with my mother-in-law and I meant to say: ‘Please pass the butter.’ But instead I said ‘You silly cow, you’ve completely ruined my life.’”

Now what's true is that even though our everyday speech is full of concepts developed and popularized by Freud, Freudian psychoanalysis (or at least the traditional form of psychoanalysis) has fallen out of favor in contemporary psychotherapy. Although it was the dominant model through the 1970s, it is a long-term, insight-oriented therapy that doesn’t fit with our contemporary understanding of what people’s problems are, what solutions they're looking for, and perhaps most importantly, how managed care pays for services.

Even still, Freudian psychoanalysis (and particularly its modern day derivatives) contains ideas that are useful to anyone who’s involved in a therapeutic relationship, including those ideas of transference, countertransference and defense mechanisms.

In the next section of this podcast, we're going to talk about Alfred Adler, who took a very different approach to understanding people’s problems and therefore [00:20:00] what the solutions to those problems are.

[End of Audio]
[0:20:02]